

Mesenchymal stem cell therapy is often described as though the cells permanently settle in damaged tissue and replace what has been lost. Current research suggests a more complex possibility. Mesenchymal stromal cells, commonly called MSCs, may work mainly by producing temporary biological signals that interact with immune, vascular, inflammatory, and repair pathways.
That distinction raises an important question about MSC therapy for neurological disease. If the biological activity produced by an MSC treatment is limited in duration while a neurological condition continues for years, could more than one exposure sometimes be biologically reasonable?
The honest answer is that repeated treatment is a scientific hypothesis, not a proven neurological treatment standard. Research has not established that an MSC series is more effective than a single treatment for Parkinson’s disease, Alzheimer’s disease, multiple sclerosis, ALS, chronic traumatic brain injury, or other neurological conditions. The appropriate cell source, dose, route, timing, and number of treatments also remain uncertain.
At Sharlin Health & Neurology in Ozark, Missouri, regenerative medicine is considered within a broader neurological plan. The goal is to examine the rationale, evidence, risks, regulatory status, and measurable patient response without presenting an investigational therapy as an established cure.
What You’ll Learn
- How MSCs may influence immune and repair pathways
- Why their biological activity may be temporary
- Why treatment timing may matter alongside cell number
- What repeated treatment studies have found outside neurology
- What the MESEMS trial found in multiple sclerosis
- Why no standard neurological MSC series has been established
- Which factors should be reviewed before another treatment is considered
Understanding what MSCs may do after administration helps put the question of treatment frequency into context.
How Mesenchymal Stem Cells May Work in the Body
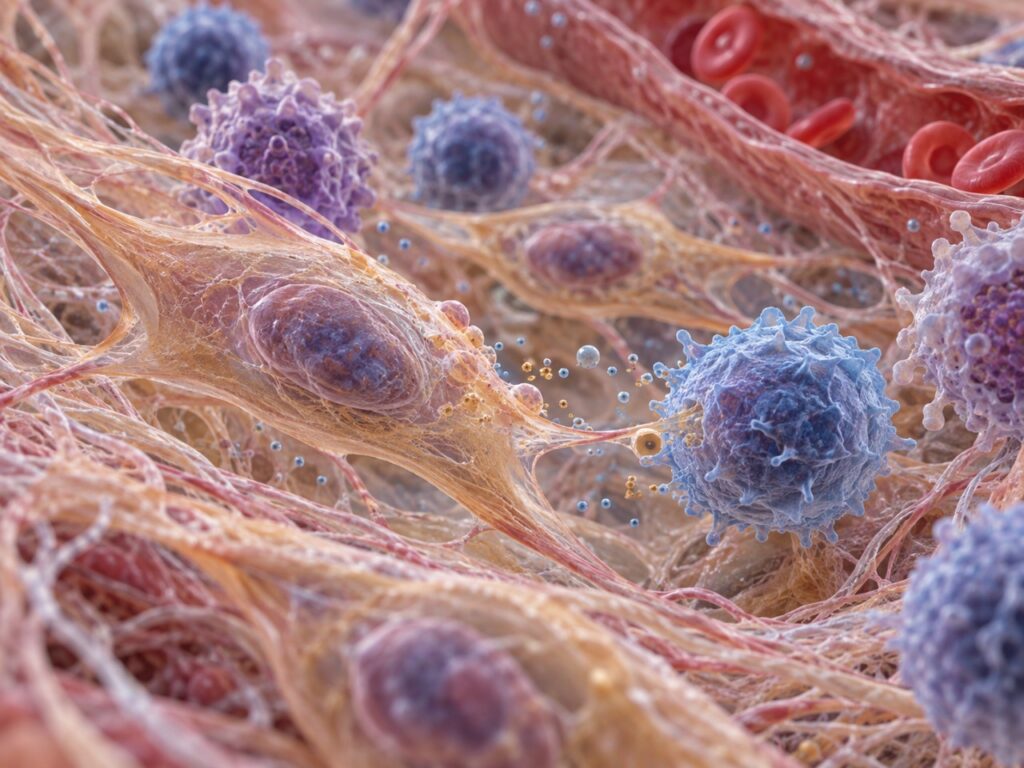
Early descriptions of stem cell therapy often focused on a replacement model. In that model, administered cells travel to injured tissue, remain there, become specialized cells, and rebuild damaged structures.
That does not appear to explain most of the effects attributed to MSCs. Following intravenous administration, many cells initially become concentrated in the pulmonary circulation. Their persistence may be limited, and long term engraftment in neurological tissue has not been established as the primary mechanism behind reported effects.
Instead, MSCs may interact with the recipient through several pathways. These can include immune modulation, communication with monocytes, macrophages, and T cells, release of signaling molecules, extracellular vesicle activity, vascular effects, and changes related to the body’s clearance of administered cells.
This supports a different way of thinking about treatment. MSCs may influence the conditions surrounding repair rather than directly rebuilding neurological tissue themselves. The patient’s own cells and biological systems would still have to carry out any lasting repair or functional adaptation.
This proposed signaling model is one reason researchers continue to examine how long an MSC-related effect may persist.
Why a Temporary Signal Does Not Prove a Series Will Work
A temporary biological effect does not automatically mean that repeating the treatment will improve clinical outcomes. That conclusion must be tested in controlled human trials for the specific condition, product, dose, route, and schedule being considered.
Repeated exposure might extend a useful biological response, provide no additional benefit, or increase adverse events and cost without improving function. MSCs obtained from different tissues or donors may not behave identically, and manufacturing, storage, viability, potency, dose, and delivery route can affect the final product.
For these reasons, serial MSC therapy should be described as an investigational dosing strategy. Biological plausibility can justify research, but it cannot substitute for evidence of patient benefit.
The chronic nature of neurological disease explains why the question is worth studying, even though the answer is not yet known.
Chronic Neurological Disease Continues After an Infusion

Conditions such as Parkinson’s disease, Alzheimer’s disease, multiple sclerosis, ALS, and chronic traumatic brain injury do not result from one biological event that ends when treatment begins. Depending on the diagnosis, disease activity may involve inflammation, immune dysfunction, oxidative stress, mitochondrial changes, vascular injury, altered metabolism, and progressive loss of cellular function. An MSC treatment might influence some pathways without correcting the full disease process.
That leads to a reasonable research question. Could appropriately timed exposure matter more than a single large cell count? The answer may differ by diagnosis and patient. A schedule that is ineffective for one neurological condition could be inappropriate for another, and benefits observed outside neurology may not transfer to brain or spinal cord disease.
The practical lesson is not that chronic disease requires repeated MSC treatment. It is that cell number alone may be an incomplete way to describe an investigational therapy.
Timing, route, potency, and patient response may all contribute to the actual biological exposure.
In MSC Therapy, Timing May Be Part of the Dose
Traditional medication dosing is usually described by quantity and frequency. Cell therapy may require an even broader model because the product is biologically active and may interact with the recipient’s changing immune and metabolic state.
A conceptual model might look like this:
Therapeutic exposure = cell number × product potency × route × recipient response × timing × number of exposures
Imagine that one patient receives 200 million cells once while another receives 50 million cells on four occasions. The cumulative cell count is the same, but the biological exposure may not be equivalent. Four treatments create four separate periods of interaction, each occurring at a different point in the patient’s clinical course.
This does not establish that divided doses are better. Only comparative trials can determine whether treatment frequency changes outcomes.
Human studies outside neurology offer limited clues, but they must be interpreted within their original clinical setting.
What Human Research Says About Repeated MSC Treatment

Some of the more direct human research comparing single and repeated MSC administration comes from knee osteoarthritis, not neurological disease.
A 2025 systematic review and network meta-analysis evaluated 16 randomized trials involving 622 patients with knee osteoarthritis. Both single and repeated MSC injections were associated with improvements in pain and knee function. In the network analysis, repeated injections ranked better for some outcomes at six and 12 months, but they were also associated with more adverse events.
The available repeated treatment studies were limited in number and size, and they concerned injections into arthritic knees. They do not establish that an MSC series improves Parkinson’s disease, Alzheimer’s disease, MS, ALS, or traumatic brain injury. They only show that treatment frequency may affect both potential benefit and cumulative risk in some settings.
The strongest neurological evidence discussed in this context comes from a different type of study with a less encouraging result.
What the MESEMS Trial Found in Multiple Sclerosis
The phase 2 MESEMS trial enrolled 144 people with active multiple sclerosis across 15 sites in nine countries. Participants received a single intravenous dose of their own bone marrow-derived MSCs or placebo, followed by the alternate intervention at week 24 in a crossover design.
The primary efficacy endpoint was the cumulative number of gadolinium-enhancing MRI lesions over 24 weeks. MSC treatment did not reduce that outcome compared with placebo. The treatment was reported as reasonably safe and well tolerated within the trial, but the investigators concluded that the findings did not support bone marrow-derived MSC treatment for active multiple sclerosis based on the measured inflammatory MRI activity.
This negative result should not be minimized. It means that the tested product, route, dose, schedule, and patient population did not meet the trial’s primary efficacy endpoint.
The trial did not compare one MSC treatment with a planned series. That leaves the serial treatment question unresolved, not validated. A lack of evidence against every possible schedule is not evidence that another schedule will work.
The current evidence can therefore be summarized more clearly in a table.
What Is Known and What Remains Uncertain
| Evidence question | What current research suggests | Important limitation |
|---|---|---|
| Do MSCs permanently replace damaged neurological cells? | Most proposed effects involve signaling and immune interaction rather than proven long-term tissue replacement | Mechanisms may vary by product, route, and disease |
| Can repeated MSC treatment outperform one treatment? | Some knee osteoarthritis research favors repeated injections for certain outcomes | Joint injection results cannot establish neurological benefit |
| Did one MSC treatment improve active MS in MESEMS? | The trial did not meet its primary MRI efficacy endpoint | It tested one product, route, dose, and schedule |
| Is a standard MSC series established for neurological disease? | No | The appropriate number and interval remain unknown |
| Does greater exposure create greater benefit? | Possibly in some settings | Greater exposure may also increase adverse events, cost, and uncertainty |
| Are MSC products approved for these neurological conditions? | No MSC product is FDA approved for the neurological uses discussed here | Patients should verify the product’s regulatory and clinical trial status |
Because the evidence is incomplete, treatment decisions cannot be reduced to a preset package or universal calendar.
Why Each Treatment Could Encounter a Different Patient

A patient’s disease activity, inflammation, sleep, metabolic health, nutrition, rehabilitation, medications, and stress can change over time. Those changes could influence treatment response. They could also create the appearance of an MSC effect when improvement is related to rehabilitation, medication adjustment, natural fluctuation, or another intervention.
This is why objective measurement matters. If an investigational treatment is considered, clinicians should define what will be measured before treatment, when reassessment will occur, and what would count as meaningful improvement or an unacceptable adverse effect.
At Sharlin Health & Neurology, the conceptual process is:
Prepare → Treat → Observe → Reassess → Repeat only when justified
The final step is conditional. It should depend on clinical findings, safety, evidence, and patient goals rather than the assumption that every person needs the same number of treatments.
That distinction separates a measured clinical process from an arbitrary treatment series.
When Another MSC Treatment Should Not Be Automatic
There is no universally established number or interval for MSC treatment in chronic neurological disease. A predetermined series should not be presented as a proven protocol when research has not established one.
Before another treatment is considered, a clinical review may examine:
- The accuracy and stage of the neurological diagnosis
- Objective changes in symptoms and function
- Disease specific measurements
- Adverse events after the previous treatment
- The durability of any observed response
- Rehabilitation and functional progress
- Changes in medication, sleep, nutrition, or metabolic health
- Cell source, identity, viability, potency, and manufacturing consistency
- Route of administration and procedure-related risk
- The patient’s goals, financial burden, and tolerance for uncertainty
- Whether another exposure remains ethically and clinically justifiable
A lack of improvement should not automatically lead to a higher dose or more treatments. It may indicate that the product, route, schedule, or treatment concept is not appropriate.
Regulatory status must also be part of the conversation.
FDA Status and Patient Safety
As of August 2026, no MSC product is FDA-approved to treat Parkinson’s disease, Alzheimer’s disease, multiple sclerosis, ALS, traumatic brain injury, or the other neurological conditions discussed in this article.
The FDA’s consumer information on regenerative medicine products warns that many products marketed as stem cell or regenerative treatments have not been shown to be safe or effective for the advertised uses. Investigational use should occur with appropriate regulatory oversight, informed consent, product documentation, and safety monitoring.
Patients should ask what the product contains, how it was manufactured and tested, whether an Investigational New Drug application applies, what evidence supports the proposed use, and how adverse events will be handled. Terms such as “natural” or “regenerative” do not establish safety or effectiveness.
Clear regulatory and scientific disclosure should occur before a financial or treatment decision is made.
The following questions can help patients understand the difference between a research rationale and a proven treatment plan.
Frequently Asked Questions
1. Is more than one MSC treatment necessary for neurological disease?
Research has not established that patients with neurological disease need a specific number of MSC treatments. A series may be biologically plausible in some circumstances, but it remains investigational and should not be presented as a proven standard.
2. Is serial MSC therapy more effective than a single treatment?
Some knee osteoarthritis studies suggest repeated injections may improve certain outcomes more than one injection, but those findings do not prove benefit for neurological disease. Direct comparative neurological trials are needed.
3. Can MSC therapy cure Parkinson’s, Alzheimer’s, MS, or ALS?
No. MSC therapy has not been proven to cure these diseases. Research continues into possible immunological, neuroprotective, and repair-related effects, but clinical benefit remains uncertain and may differ by condition.
4. What did the MESEMS trial show?
The MESEMS trial found that one intravenous dose of autologous bone marrow-derived MSCs did not reduce cumulative gadolinium-enhancing MRI lesions in active multiple sclerosis. The treatment was reasonably well tolerated, but the primary efficacy endpoint was not met.
5. What are the risks of repeated MSC treatment?
Risk depends on the product, route, dose, patient, and procedure. Concerns may include infection, immune or infusion reactions, vascular complications, contamination, product inconsistency, procedural injury, and cumulative financial burden.
6. Is MSC therapy FDA approved for neurological disease?
No MSC product is FDA-approved for the neurological conditions discussed in this article. Patients should verify regulatory status and should not assume that availability means FDA approval.
These answers underscore why neurological evaluation and informed consent must come before any decision about investigational treatment.
A Measured Approach to Investigational Regenerative Neurology
The biological rationale for studying serial MSC therapy is understandable. MSCs may act mainly through temporary signaling, while chronic neurological disease continues over time. Treatment frequency may therefore deserve study as part of the total dose.
What remains unproven is whether repeating MSC treatment improves neurological function, slows disease progression, or produces benefits that outweigh its risks and costs. Evidence from knee osteoarthritis cannot answer that question, and the MESEMS trial did not support a single intravenous MSC treatment for active MS on its primary MRI outcome.
At Sharlin Health & Neurology, we approach regenerative medicine as a process rather than a promise. Through a detailed neurological evaluation, objective measurement, careful risk review, and individualized planning, we help patients understand what is known, what remains uncertain, and what questions to answer before considering an investigational therapy.
If you are exploring regenerative medicine for a chronic neurological condition, schedule a consultation with Sharlin Health & Neurology in Ozark, Missouri. A consultation can help you review the evidence, regulatory status, possible risks, and whether regenerative care fits within your broader neurological plan.
Regenerative cell therapies remain investigational for the neurological conditions discussed in this article. As of August 2026, no FDA-approved MSC product exists for these neurological indications. Discussion of biological rationale does not establish clinical efficacy or a standard treatment schedule.Explore why serial MSC therapy may be considered for neurological disease, including its biological rationale, current evidence, risks, and limits.
